Surgical technology is changing quickly, but responsible buying requires more than following impressive headlines. Hospitals and distributors now examine clinical value, workflow safety, training demands, and long-term maintenance. The key question is: what are the latest trends in surgical technology, and which developments genuinely improve patient care?
Current market movement includes robotic-assisted systems, AI-supported imaging, digital navigation, augmented reality, and smarter operating-room integration. These tools can improve visualization and procedural consistency when properly validated. For example, a navigation platform may combine preoperative scans with real-time instrument tracking. A surgeon can then view anatomy on a monitor while planning each movement. Small details matter.
However, innovation does not automatically mean better outcomes. Buyers should review peer-reviewed evidence, regulatory clearances, cybersecurity controls, service agreements, and staff training requirements. They should also ask whether a system fits existing imaging equipment and hospital information networks. An expensive platform may create delays if technicians cannot maintain it locally. That risk is often underestimated.
This guide evaluates China’s latest surgical technology trends from a practical buyer’s perspective. It considers manufacturer experience, product reliability, clinical partnerships, and after-sales support. Factory demonstrations can be useful, but they cannot replace independent clinical assessment. Some market claims remain difficult to verify. Careful comparison is essential. Buyers should request transparent specifications, realistic performance data, and references from comparable hospitals. The strongest purchasing decisions balance innovation with evidence, affordability, patient safety, and measurable workflow improvements. Trends may change again soon. That is precisely why cautious judgment matters.
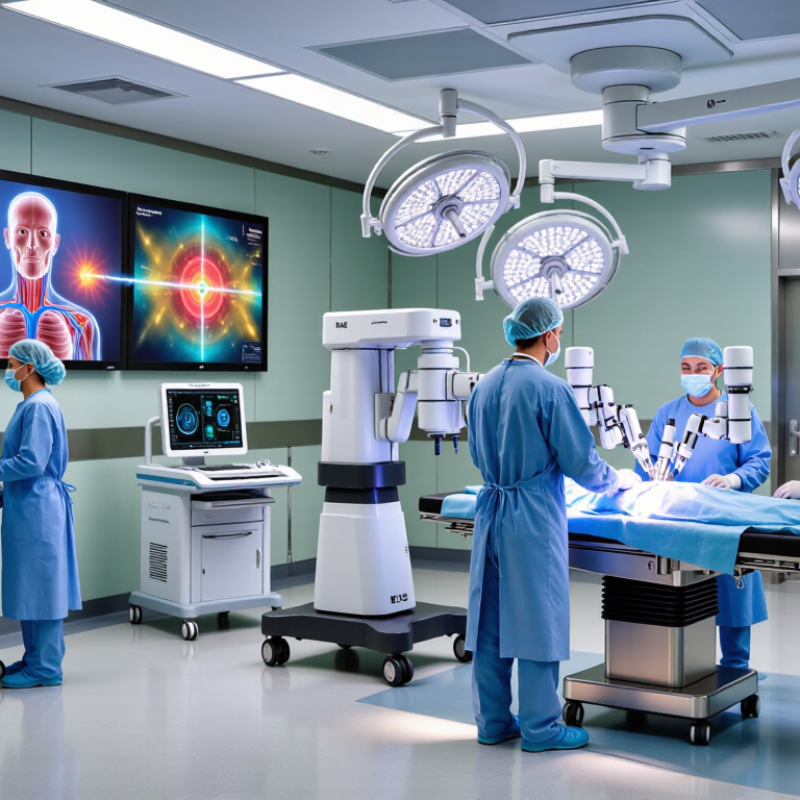
China’s latest surgical technology landscape is moving from isolated innovation toward connected operating-room systems. Hospitals are adopting robotic assistance, high-definition endoscopy, 3D visualization, and image-guided navigation. Artificial intelligence is entering surgical planning, lesion measurement, and postoperative monitoring. Yet adoption varies sharply between major urban hospitals and smaller regional centers. Buyers should examine clinical workflow, not only equipment brochures.
A modern operating room may combine ceiling-mounted displays, digital anesthesia records, sterile tracking, and real-time imaging. Surgeons increasingly expect instruments that support smaller incisions and controlled movement. Procurement teams also evaluate local servicing, staff training, cybersecurity, data compatibility, and sterilization cycles. These details affect uptime. A technically advanced system can still underperform when interfaces are confusing or replacement parts arrive slowly.
Evidence matters more than novelty. Buyers should request published clinical evidence, local registration information, post-market safety records, and transparent maintenance terms. Pilots can mislead. A successful demonstration may not reflect routine use under staffing pressure. Artificial intelligence also requires careful review, especially when training data lacks regional diversity. China’s market offers strong manufacturing capacity and rapid engineering improvements, but hospitals still need independent clinical judgment, realistic budgets, and measurable outcomes before wider adoption.
China’s surgical technology sector is moving beyond basic equipment upgrades. Emerging systems now combine robotic assistance, high-definition endoscopy, and three-dimensional imaging. These tools can improve instrument control and help surgeons view narrow anatomical spaces. However, better images do not automatically produce better outcomes.
Artificial intelligence is also entering preoperative planning and intraoperative decision support. Some platforms can process scans, highlight anatomical structures, or suggest surgical pathways. Buyers should ask how the algorithm was trained, independently validated, and updated. Clear audit trails matter. So does human control. A system that offers fast recommendations may still struggle with unusual anatomy or incomplete patient data.
China is also developing compact surgical devices for hospitals with limited operating-room space. Modular designs can simplify installation and maintenance. Wireless monitoring, digital recording, and remote training may support wider clinical use. Yet interoperability remains a practical concern. Can the device exchange data safely with existing hospital systems? Are replacement parts available locally? Is staff training documented and measurable?
Procurement teams need more than a polished demonstration. They should review clinical evidence, sterilization procedures, cybersecurity controls, and post-market support. Trial use under real workflow conditions is valuable. My concern is that some evaluations still emphasize technical performance over patient-centered results. That gap deserves closer scrutiny. Real progress will depend on reliable evidence, transparent limitations, and surgeons who can challenge the technology when necessary.
China’s latest surgical technology trends are reshaping clinical practice across major specialties. In general surgery, minimally invasive platforms support smaller incisions, clearer visualization, and more controlled tissue handling. Image guidance can help surgeons locate lesions during liver, pancreatic, and colorectal procedures. However, outcomes still depend on anatomy, training, and patient selection.
Orthopedic teams use navigation and three-dimensional planning for joint replacement and spinal procedures. Neurosurgeons apply real-time imaging to improve accuracy near sensitive structures. In gynecology, advanced endoscopic systems can support complex pelvic operations with reduced tissue disruption. Cardiovascular surgeons increasingly assess digital imaging, perfusion data, and catheter-based options before treatment. These tools offer value, but clinical evidence should guide adoption. A sophisticated system cannot correct weak surgical judgment.
Tips: Buyers should request peer-reviewed evidence, procedure-specific results, and transparent maintenance terms. Check whether the technology fits existing operating rooms, sterilization workflows, and hospital information systems. Ask surgeons to test the interface with realistic training models. Training time is often underestimated. Also examine failure procedures, data security, and technical support during urgent cases. Early pilot programs may reveal workflow delays that product demonstrations hide. Cost per procedure matters more than purchase price. In some hospitals, a simpler device may deliver safer and more consistent results. Further review is necessary when claimed benefits rely mainly on laboratory testing rather than long-term clinical follow-up.
China’s latest surgical technologies deserve careful assessment, not showroom enthusiasm. Buyers should request peer-reviewed clinical evidence, adverse-event data, and post-market surveillance records. The WHO reports that one in ten patients experiences harm during healthcare, with more than half considered preventable. Safety must remain measurable.
Ask whether the device improves outcomes, reduces operating time, or only adds visual sophistication. A 2024 ECRI health technology report highlights risks linked to connected medical equipment, including cybersecurity and interoperability gaps. Buyers should test data transfer, alarm behavior, sterilization processes, and emergency overrides in a simulated operating room. Small details matter.
Check compatibility with existing imaging systems, operating tables, software, and staff training. Require risk files aligned with ISO 14971 and electrical safety evidence under IEC 60601 where applicable. Independent validation is stronger than supplier demonstrations. Regulatory clearance is important, but it does not prove superiority for every procedure.
Be cautious with impressive early studies. Small samples can hide complications. Real-world performance may differ across hospitals. This is easy to underestimate. Ask for follow-up duration, patient selection criteria, missing data, and revision rates. A practical trial with surgeons, nurses, biomedical engineers, and infection-control staff can reveal problems before purchase. The best decision may still be delayed when evidence remains incomplete.
| Technology trend | Typical clinical use | Potential value | Safety and evidence checks | Compatibility and procurement checks |
|---|---|---|---|---|
| Robot-assisted surgery | Selected minimally invasive procedures, depending on the system’s approved indications and local clinical practice. | May provide instrument articulation, a magnified three-dimensional view, and ergonomic support for the surgeon. | Review the approved indication, clinical evidence for the specific procedure, training requirements, emergency conversion plan, and system maintenance records. Do not assume better outcomes for every procedure. | Check operating-room space, compatible instruments and accessories, installation requirements, service response, consumable availability, and total cost per procedure. |
| 3D and 4K endoscopic imaging | Laparoscopic and endoscopic procedures requiring visualization of anatomy and instruments. | Higher-resolution or stereoscopic imaging may help clinicians distinguish structures and judge depth, subject to the procedure and user experience. | Assess image performance under realistic lighting, smoke, and motion conditions. Confirm cleaning, disinfection, and sterilization instructions for reusable components. | Verify connections and interoperability among the camera head, scope, light source, display, recording equipment, and existing operating-room setup. |
| Fluorescence-guided imaging | In selected procedures, fluorescence imaging can assist visualization of perfusion, anatomy, or other targets when used with an appropriate imaging agent and approved protocol. | Adds an imaging mode that may provide information not visible under standard white light. | Check the authorized indications and instructions for both the imaging system and any imaging agent. Review contraindications, adverse-event information, and evidence for the intended clinical question. | Confirm the system supports the required imaging mode and that compatible scopes, filters, agents, and software are available for the intended workflow. |
| Image-guided navigation | Selected procedures in which instruments or anatomy are tracked or displayed in relation to preoperative or intraoperative images. | May support localization and procedural planning; performance depends on registration accuracy and clinical conditions. | Ask for accuracy data and the test conditions behind it. Review registration steps, drift detection, failure warnings, and the plan for continuing safely if navigation is unavailable. | Check compatibility with imaging formats, instruments, tracking equipment, room layout, and the hospital’s imaging and data workflows. |
| Advanced energy devices | Cutting, coagulation, sealing, or tissue dissection in open and minimally invasive surgery, within the device’s approved use. | Different energy modalities and instrument designs can support specific tissue-management tasks. | Review intended tissue types, activation controls, thermal-spread and safety information, relevant clinical evidence, and staff training. Confirm inspection and maintenance procedures. | Confirm generator and handpiece compatibility, connector type, reusable or single-use status, and the ongoing cost and supply of validated accessories. |
| AI-enabled imaging and surgical software | Depending on the product, software may support image analysis, workflow assistance, or planning; its role varies by intended use. | May help organize or interpret information, but should not be assumed to replace clinician judgment. | Verify the software’s intended use and regulatory status. Request evidence for the target population and task, assess limitations and update controls, and establish human review and incident reporting procedures. | Assess integration with hospital systems, cybersecurity controls, access permissions, data storage location, privacy requirements, and the impact of software updates. |
Buyer note: For products supplied in China, verify applicable registration or filing information and the authorized intended use through official regulatory channels. Request current labeling, clinical evidence, risk-management information, training materials, service terms, and a documented compatibility assessment before procurement. Technology availability and approved indications may vary by product and change over time.
China’s latest surgical technology is moving toward minimally invasive platforms, image guidance, and data-assisted workflows. Buyers should evaluate suppliers beyond technical specifications. The Lancet Commission on Global Surgery estimated that five billion people lack access to safe, affordable surgical care, with 143 million additional procedures needed annually. This gap increases demand, but procurement mistakes remain expensive.
Request a total-cost-of-ownership model. Include installation, training, disposable instruments, software updates, calibration, and equipment downtime. A low initial quote can become costly after two years. Supplier assessment should cover manufacturing quality, regulatory documentation, clinical references, and spare-parts availability. After-sales support deserves measurable terms, such as remote response within four hours and on-site service within 48 hours. These targets should appear in the contract. The WHO Global Patient Safety Action Plan 2021–2030 also supports stronger training, risk management, and incident reporting.
Tips: Compare at least three suppliers. Ask for five-year operating costs. Test the user interface with surgeons and nurses. Check service records, not only promises. Confirm whether local engineers can repair critical modules. A demonstration may look perfect, yet daily workflow can expose delays. Buyers should also request cybersecurity policies and upgrade conditions. No scorecard is perfect; clinical staff may value simplicity more than advanced functions. That assumption needs review before purchase.
Hospitals are adopting robotic assistance, high-definition endoscopy, 3D visualization, and image-guided navigation. Some rooms also use ceiling displays and digital anesthesia records.
Image guidance can help locate lesions during liver, pancreatic, and colorectal procedures. Orthopedic teams may use 3D planning for joint replacement and spinal surgery.
Ask for peer-reviewed studies, procedure-specific outcomes, adverse-event data, and post-market safety records. Small samples can hide complications.
Test interfaces with realistic training models and staff from several departments. Check sterilization cycles, data transfer, and emergency overrides.
Review how the tool measures lesions or supports planning, and check the diversity of its training data. Real-world results may differ.
Slow replacement parts or unclear interfaces can reduce uptime. Training takes time. Ask about local technical support and staff preparation.
Compare cost per procedure, maintenance, training, and compatibility—not only the purchase price. A simpler device may be more consistent.
A practical trial can expose workflow delays that a demonstration misses. A polished demo can still mislead; that is easy to overlook.
China’s surgical technology landscape is evolving through the integration of minimally invasive techniques, robotic assistance, advanced imaging, digital navigation, smart instruments, and data-supported clinical workflows. For buyers asking, “what are the latest trends in surgical technology,” the key developments include improved precision, smaller incisions, enhanced visualization, faster recovery pathways, and greater use of connected systems. These technologies are being explored across general surgery, orthopedics, cardiovascular procedures, neurosurgery, gynecology, and other specialties, with applications adapted to different hospital environments and clinical needs.
Before purchasing, buyers should assess safety records, clinical evidence, regulatory status, user training requirements, system compatibility, maintenance needs, and data protection practices. Procurement decisions should also consider supplier reliability, total ownership costs, consumables, installation, staff education, technical support, warranty coverage, and long-term after-sales service. A structured comparison of performance, evidence, workflow benefits, and lifecycle value can help healthcare organizations select suitable solutions while supporting responsible and sustainable adoption.

Seeker Medical